
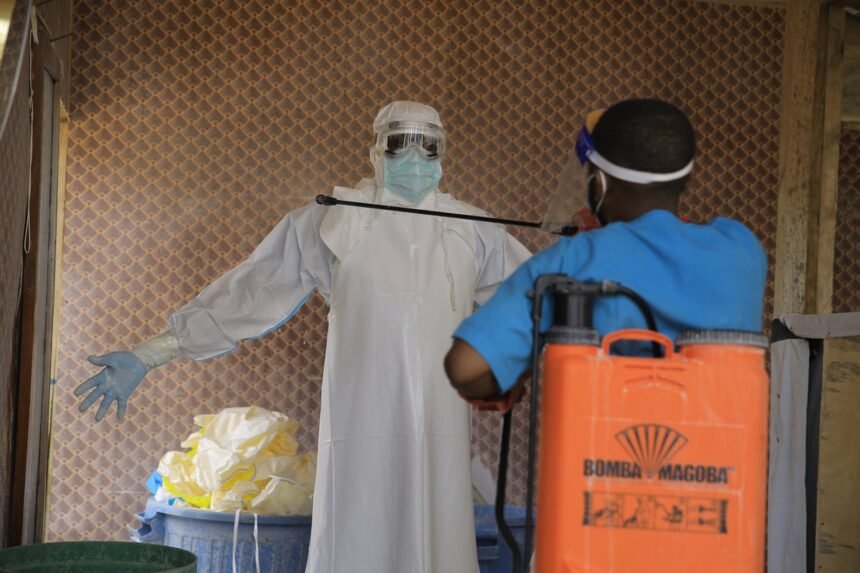
The largest and deadliest Ebola epidemic ever recorded in the Democratic Republic of Congo has now crossed into three neighbouring nations, prompting a stark warning from the continent’s top public health official that the virus could follow a Covid-style trajectory to Europe and the UK unless every government immediately raises its preparedness. Dr Jean Kaseya, director general of the Africa Centres for Disease Control and Prevention, said the outbreak — driven by the rare Bundibugyo strain — has already claimed nearly 5,000 lives from more than 10,000 confirmed cases since it ignited in mid-May. With a single imported case already detected in France, the message from Kinshasa is unambiguous: no border can guarantee safety if the international community treats this as a distant crisis.
Unprecedented Scale and Geographic Reach
This is the seventeenth time Ebola has surfaced in the DRC since the virus was first identified there in 1976, but epidemiologists say the current event is unlike any predecessor. For the first time in recorded history, three distinct African regions — Central, East, and West Africa — are simultaneously battling active transmission chains linked to a single outbreak.
The virus has moved with alarming speed. Kenya confirmed its index case earlier this month after a traveller arriving from Congo via Uganda died in Nairobi; eight further infections were subsequently identified. Last week, Nigeria became the fourth African nation to report a case. France remains the only non-African country with a confirmed infection, recorded in June when a doctor returned from the DRC, but Dr Kaseya insists that isolation is an illusion.
“We shouldn’t forget that at the beginning of Covid, many countries said there was zero risk of being affected, but a few months later, they became the hotspot,” he told The Guardian. “We don’t want to see the UK and other countries become the hotspot.”
The Bundibugyo Strain: What We Know
The pathogen driving the crisis is the Bundibugyo species of Ebolavirus, first isolated during a 2007 outbreak in Uganda. Its case fatality ratio ranges between 21 and 50 per cent — lower than the notorious Zaire species, but still devastating in settings where intensive care is scarce.
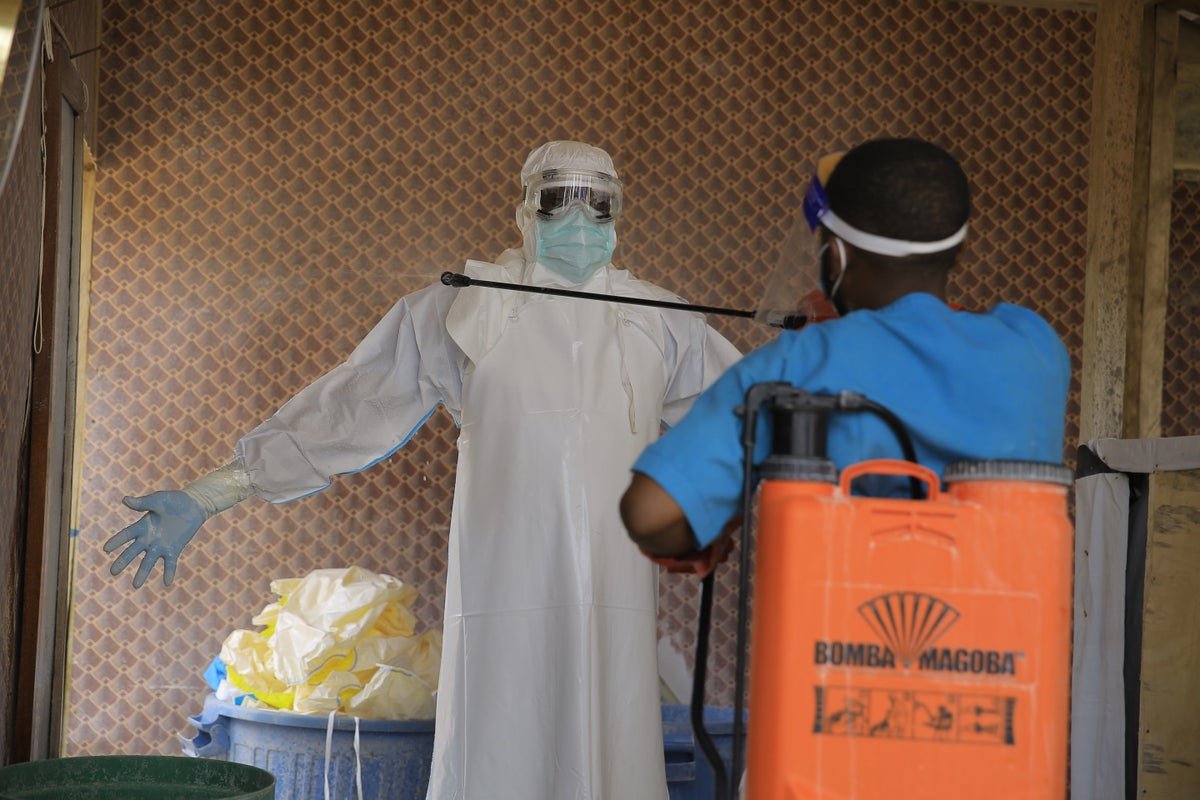
Clinically, the illness begins with non-specific misery: muscle aches, high fever, headache and sore throat. Within days, many patients progress to severe vomiting and diarrhoea, driving rapid dehydration and electrolyte collapse. Transmission requires direct contact with the blood, vomit, faeces or other body fluids of symptomatic individuals, or with the remains of those who have died. It does not spread through casual contact or airborne routes, a fact that offers a sliver of reassurance for infection-control planning but demands rigorous barrier nursing and safe burial practices.
There is currently no licensed cure. Supportive care — aggressive fluid resuscitation, electrolyte correction, and management of secondary infections — remains the mainstay of treatment. However, scientists at the University of Oxford are working at pace on a candidate vaccine tailored to the Bundibugyo glycoprotein, which could be deployed under emergency protocols should the epidemic spiral further.
Conflict and Displacement Fuel the Crisis
Containment in eastern DRC is being crippled by a humanitarian catastrophe. Protracted armed conflict has uprooted hundreds of thousands of civilians, destroying health infrastructure and severing the trust between communities and responders. Vaccination teams cannot reach insecure zones; contact tracing collapses when populations are mobile and fearful.
Dr Kaseya intends to table a formal appeal for a “corridor of peace” at a summit of African heads of state scheduled for November. The concept — a negotiated humanitarian pause in hostilities to allow vaccinators and epidemiologists safe passage — has precedent in polio eradication campaigns but has proven elusive in the Kivus. Without it, the virus will continue to exploit the chaos.
Funding Gaps and the Race for a Vaccine
The financial architecture of the response is equally fragile. International donors — led by the United States, the United Kingdom, and the European Union — have pledged a combined $3 billion (£2.3 billion). Yet more than two-thirds of that sum remains undisbursed, leaving a yawning operational gap. African member states have collectively committed $120 million, a significant show of solidarity but insufficient against the scale of need.
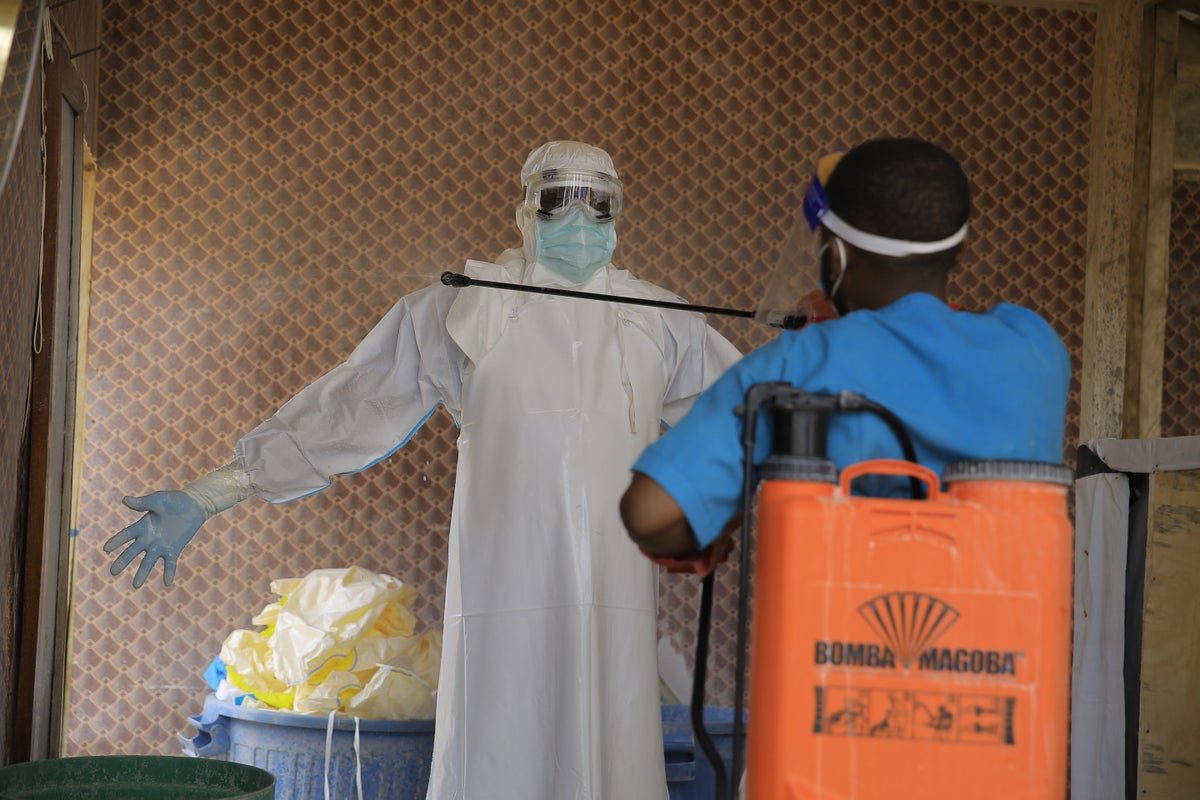
Every week of delayed funding translates into missed vaccination rings, stockouts of personal protective equipment, and unpaid community health workers. The Oxford vaccine programme, while promising, requires sustained investment to complete Phase II/III bridging studies and establish manufacturing capacity for regional supply.
Why it Matters
This outbreak is not a remote tragedy; it is a stress test for the global health security architecture built painfully over the last decade. The Bundibugyo strain’s lower lethality must not breed complacency — its ability to traverse conflict zones, cross porous borders, and seed cases on another continent proves that geography is no longer a shield. If the world waits for a case in London or Manchester to act, the window for containment will have slammed shut. The “corridor of peace” Dr Kaseya seeks is more than a diplomatic gesture; it is a prerequisite for stopping a virus that feeds on fragmentation. Funding pledges must become bank transfers, and pandemic preparedness plans must move from paper to practice. The cost of prevention now is a fraction of the cost of response later — measured not only in pounds, but in lives.


