
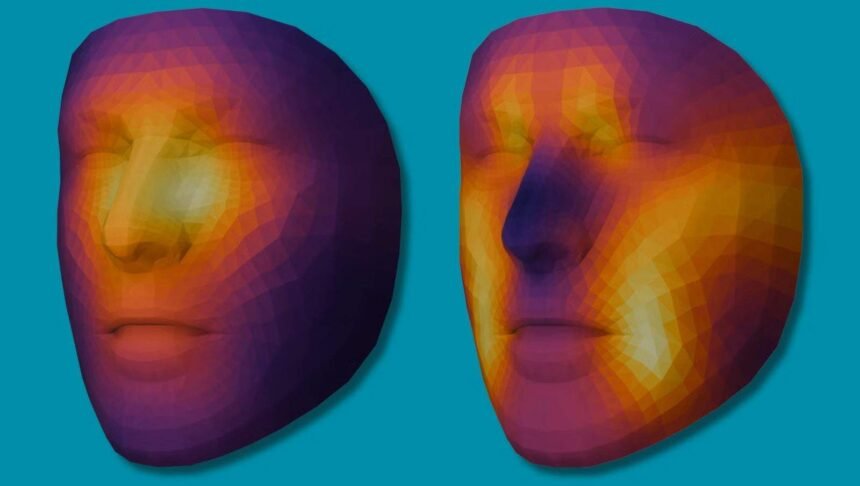
A new study published in The Lancet on Monday reveals that artificial‑intelligence models can estimate a person’s biological age and likelihood of surviving cancer treatment using just a single photograph of their face. Researchers trained the systems on a dataset of 40 million images, incorporating facial data from more than 30 000 cancer patients and their outcomes. The work has sparked both excitement and caution, with the team launching a public website that has already gathered roughly 50 000 submissions in its first few days.
Training the Algorithms on a Massive Visual Dataset
The research team, led by Dr Raymond Mak from the Mass General Brigham Cancer Institute and its Artificial Intelligence in Medicine programme, assembled an unusually large repository of visual information. Over 40 million photographs were fed into the machine‑learning pipeline, a significant portion of which carried age annotations. In parallel, the scientists compiled more than 30 000 images of cancer patients together with detailed clinical outcomes. This dual‑layered dataset allowed the models to learn both general facial ageing patterns and disease‑specific markers. The scale of the training set is unprecedented in facial‑analysis research, giving the algorithms a broad reference frame from which to infer health signals.
Decoding the Facial Clues for Age and Mortality
When the models were applied to the cancer cohort, they produced two distinct predictions: an estimate of biological age and a forecast of mortality risk. Dr Mak explained that the age‑estimation component focused on the temples, the forehead and the nasolabial fold, while the mortality predictor highlighted the bridge of the nose and the areas beneath the eyes. To understand how the system arrived at these judgments, the researchers employed interpretability techniques that essentially asked the algorithm which facial regions were most influential for each prediction. This “explainability” step is crucial, as it offers a window into the otherwise opaque decision‑making process of deep‑learning models.
The findings echo a practice familiar to clinicians: doctors routinely make subjective health assessments simply by looking at a patient. As Dr Mak noted, “Doctors are trained from the very beginning of medical school to make subjective assessments of people’s health, to guide decision‑making. You walk in the room, you eyeball them and you document.” The AI approach aims to replicate and augment this instinctual evaluation, potentially providing an objective, data‑driven counterpart to the clinician’s gut feeling.
Clinical Promise Meets Skepticism
Despite the optimism, independent experts caution that the technology is not yet ready for bedside use. Professor Miroslaw Bober of the University of Surrey, commenting through the Science Media Centre, warned that “Predicting an outcome is not the same as explaining it. Despite the references to ‘biological age’, the AI estimates age from facial appearance rather than directly measuring any underlying biological ageing process.” He further pointed out that the study did not demonstrate whether the AI recognised anything a doctor would miss, nor whether the predictions added clinically useful information beyond standard assessments of a patient’s general health and fitness—factors that were not measured in the trial.
The cautious stance reflects a broader debate in digital health: while AI can uncover patterns invisible to the human eye, its black‑box nature and lack of validation in real‑world settings mean that integration into clinical pathways must be gradual and rigorously tested.
Ethical Safeguards and Public Response
Beyond the science, the researchers have been mindful of the privacy and ethical ramifications of training models on facial data. Dr Mak highlighted the consent dilemma: “There’s a privacy issue of did the patient consent or assent to having their data either collected or analysed, and then what do people do with that information?” He warned that misuse could lead to denial of medical insurance or further rationing of care. Recognising these risks, the team decided to proceed with the research only after engaging ethicists and regulatory bodies to establish “guardrails” before the technology could be exploited.
Public interest has been swift. Accompanying the journal publication, the researchers launched a website where anyone could upload a photo and receive an estimate of their biological age. By Wednesday morning, the platform had processed around 50 000 submissions, illustrating both the curiosity and the appetite for accessible health insights. This rapid uptake underscores the potential for AI‑driven diagnostics to democratise healthcare, yet it also amplifies the responsibility to ensure transparency, consent, and equitable access.
Why it Matters
The ability to infer serious health outcomes from a simple selfie could revolutionise early disease detection, especially in settings where conventional diagnostics are scarce. If validated, such tools could enable low‑cost, widely accessible screening that empowers individuals to monitor their health trajectory over time. However, the path from laboratory breakthrough to clinical practice is fraught with scientific, ethical, and regulatory challenges. Ensuring that AI predictions are both accurate and interpretable, that patient privacy is robustly protected, and that the technology is deployed equitably will determine whether this promising research translates into tangible public‑health benefits or remains a fascinating scientific curiosity.

