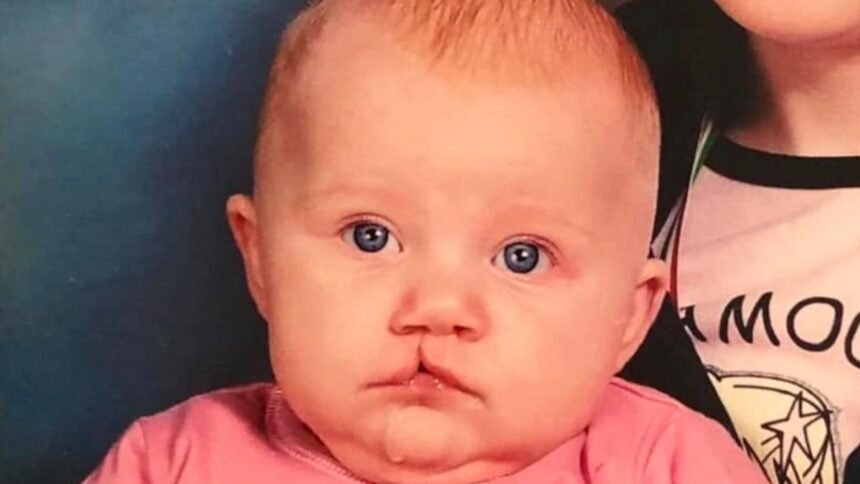
A Cardiff mother has spoken candidly about the “invisible wall” of social isolation she faced growing up with a cleft lip, reigniting a urgent conversation about the psychological aftercare offered to thousands of British children born with the condition each year. While surgical repair is routinely successful on the NHS, advocates warn that the emotional architecture of a patient is too often left unrepaired.
The condition affects approximately one in every 700 babies born in the UK, making it one of the most common congenital anomalies. Yet, as 34-year-old Sian Evans explains, the clinical pathway frequently ends at the operating theatre door, leaving patients to navigate a world of staring, whispering, and workplace discrimination entirely alone.
The Long Shadow of the Playground
For Sian, the memory of primary school in the Valleys remains visceral. She describes a childhood defined not by the surgeries — she lost count after the seventh — but by the silence that followed her into a room.
“It wasn’t the operations that broke me,” she says, her voice steady but quiet. “It was the birthday parties I wasn’t invited to. It was the parents who pulled their children away in the supermarket aisle. I felt ostracised, not because of my lip, but because of other people’s fear of it.”
That fear manifests early. Research from the Cleft Lip and Palate Association (CLAPA) indicates that children with visible facial differences are significantly more likely to experience bullying by age ten. The psychological toll often tracks into adulthood, correlating with higher rates of social anxiety and lower employment outcomes compared to the general population.
Sian recalls a pivotal moment at fourteen. A consultant handed her a mirror post-surgery and declared the result “excellent.” She looked at the reflection and saw only the scar. “Nobody asked me how I felt inside,” she says. “They only measured the millimetres.”
A System Designed for Repair, Not Recovery
The NHS pathway for cleft care is world-leading in its surgical coordination. Centralised into eleven specialist centres across the UK — including the Welsh Centre for Burns and Plastic Surgery at Morriston Hospital in Swansea — the model ensures that multidisciplinary teams of surgeons, orthodontists, and speech therapists manage the physical trajectory from infancy to adulthood.

But the psychological component remains inconsistently funded.
“We have clinical psychologists embedded in the teams, but their caseloads are staggering,” explains Dr. Rhys Morgan, a consultant clinical psychologist specialising in appearance-related distress at the University Hospital of Wales. “We see the children at key transition points — starting school, moving to secondary, leaving for university. But the day-to-day grind of stigma? That happens in the gaps between appointments.”
Current NICE guidelines recommend psychological support be available at all stages. In practice, provision varies wildly by postcode. A 2023 audit by the Cleft Development Group found that while 90% of centres had access to a psychologist, only 40% met the recommended staffing ratios for their patient population.
The “Cosmetic” Trap
Complicating matters further is the persistent classification of secondary revision surgeries — often sought to refine nasal symmetry or reduce scar visibility — as “cosmetic” rather than “reconstructive” by some Integrated Care Boards.
This distinction carries weight. It determines whether a patient accesses treatment on the NHS or faces a private bill running into thousands of pounds.
“The label ‘cosmetic’ implies vanity,” argues Anna Martindale, Head of Policy at Changing Faces. “For someone with a cleft, revision surgery isn’t about chasing an aesthetic ideal. It’s about aligning their outer self with their inner identity. It’s about walking into a job interview and being seen for their CV, not their scar.”
Sian knows this battle intimately. At twenty-six, she fought a two-year battle for a nasal revision. The board initially denied funding. She won on appeal, but the process compounded the very distress the surgery sought to alleviate. “Having to prove your face is ‘broken enough’ to fix is a humiliation I wouldn’t wish on anyone,” she says.
Finding Voice in the Silence
Today, Sian runs a peer-support group in Cardiff funded by a small National Lottery grant. The room is filled with parents of newborns — terrified, grieving the “perfect” baby they imagined — and adults who have never met another person with a cleft.

“We laugh a lot,” she smiles. “Dark humour is our love language. But we also talk about the things the leaflets don’t cover. How to handle a Tinder date. Whether to disclose on a job application. How to parent when you’re still healing yourself.”
The group represents a growing movement: patient-led advocacy demanding that “whole person” care becomes the standard, not the exception. They are calling for ring-fenced funding for psychological services within cleft centres, mandatory anti-bullying training in schools referencing visible difference, and a review of the “cosmetic” threshold for revision surgery.
Why it Matters
A cleft lip is repaired in hours, but the social fracture it exposes can last a lifetime. Sian’s story is not an outlier; it is a data point in a systemic failure to treat the psyche with the same rigour as the palate. Until the NHS and wider society recognise that visible difference requires invisible support — funded, consistent, and stigma-free — thousands of British children will continue to grow up feeling like ghosts in their own classrooms, waiting for an invitation that never comes.